Category: Uncategorized

  • The Mechanisms Linking Nutrition and Mental Health

    Managing Psychosocial Risks (Digital Badge). Free for a limited time – Access here.


    >
    Blog
    >
    The Mechanisms Linking Nutrition and Mental Health


    Mental Health


    Wellbeing

    The Mechanisms Linking Nutrition and Mental Health

    wavy

    How exactly does your nutrition impact your mood and mental health? Three biological processes hold the answer.

    By Well Excel. 01 February, 2023.

    10 min read

    In a previous post we explored the link between nutrition and mental health. Research from the new field of nutritional psychiatry has shown that high quality nutrition improves mental health, and can even lead to remission of depression in some patients (Jacka et al., 2017). But how? In this post we will dive into the mechanisms. There is mounting scientific evidence that three biological processes play a central role. These are inflammation, the gut microbiome and neuroplasticity.

    Inflammation

    When we are injured or our body is infected with a pathogen like a bacterium or virus, our immune system springs into action by creating inflammation. When this response flares up and then dies down it’s called acute inflammation. Acute inflammation only affects the localized area of the body under attack. This “good inflammation” limits the spread of pathogens, destroys the invaders and begins healing damaged tissues.

    But sometimes the inflammatory response flares up and doesn’t completely die down, creating a long-lasting, low-grade activation of the immune system. This systemic (whole-body) chronic inflammation is a problem because there is growing evidence that both mental health conditions like depression and brain health conditions like Alzheimer’s are inflammatory diseases (Belliveau et al., 2022; Berk et al., 2013; Guzman-Martinez et al., 2019).

    Where exactly does this inflammation come from? Berk and colleagues (2013) conducted a review of the scientific literature and identified a poor diet and physical inactivity among the many factors associated with systemic inflammation. By contrast, the Mediterranean diet has been shown to be anti-inflammatory by measuring a range of biomarkers such as C-reactive protein, homocysteine and interleukin-6 in the blood of clinical trial participants (Chrysohoou et al., 2004).

    The Mediterranean diet is a rich source of omega-3 fatty acids and antioxidant phytochemicals (colorful plant pigments). Omega-3 fatty acids are precursors to molecules involved in signaling the end of the inflammatory process whereas antioxidants play a role in the prevention of inflammation (Monash University, n.d.).

    Gut microbiome

    We host a diverse array of microbes (microorganisms too small to be seen without a microscope) on our skin surface and in our digestive, respiratory, urinary and reproductive tracts (Liang et al., 2018). Another name for the collection of ‘bugs’ in and on our body is the microbiota. Our microbiota includes bacteria, archaea, fungi, viruses and protozoa (Sender et al., 2016).

    According to the most recent estimates, there are 30 trillion (30,000,000,000,000) cells in the human body, but we host around 38 trillion bacterial cells (Sender et al., 2016). This means human cells are outnumbered by bacterial cells. Put another way, we are only about 43% human (Gallagher, 2018)!

    There is an alternate calculation. The sum total of the genetic material (called the genome) of the human body is hard to pin down, but believed to be around twenty thousand genes (Willyard, 2018). By contrast the microbiome (the genetic material of our microorganisms) includes between two and twenty million genes (Gallagher, 2018). So, genetically, we are even more outgunned.

    What all of this means is that although we tend to think of ourselves as a single species, Homo sapiens, we are actually a superorganism: a communal group of human cells and microbial species working together for the benefit of both (Dietert, 2016). “Good bacteria” are referred to as probiotics and include Lactobacillus (also known as Acidophilus) and Bifidobacteria species. They help our body digest food, absorb nutrients and fight “bad” organisms that cause disease (pathogens) (Duggal, 2017; Robertson, 2017; WebMD, 2020). A more diverse microbiome, one with more species of microorganisms, is considered healthier.

    Traditional diets include fermented foods such as yogurt, aged cheese, pickles, kefir, sauerkraut, kimchi and sour cream. These foods are a source of probiotic bacteria. By consuming different types of fermented foods, we can introduce a more diverse array of naturally occurring probiotics and therefore improve our gut microbiota composition (Food and Mood Centre & Deakin University, n.d.).

    Our bodies are unable to digest the dietary fiber in the Mediterranean diet. However, our microbes rely on this fiber as a food source. (We call dietary fiber a prebiotic as it feeds probiotic microorganisms.) When consuming fiber, the probiotic microorganisms produce waste products called short chain fatty acids (SCFAs). These are vitally important to our health as they are both anti-inflammatory (Campos-Perez & Martinez-Lopez, 2021) and thought to act directly on the brain (Silva et al., 2020).

    One of the largest sites harboring the microbiota is the gastrointestinal tract, or ‘gut’. Scientists are just beginning to understand the enormous role that the gut microbiota plays in regulating the development and function of our immune, metabolic and nervous systems. Through these systems the gut microbiota influences the cognitive and emotional centers of the brain. The influence also happens in the other direction with the brain influencing the gut (Food and Mood Centre & Deakin University, n.d.). This bidirectional communication is referred to as the microbiota-gut-brain axis (Morais et al., 2021).

    The human microbiome can be challenged by changes in diet, particularly those associated with modern dietary habits and food production methods (Liang et al., 2018). The microbiome is also affected by stress and antibiotics (Clapp et al., 2017). Such assaults can cause dysbiosis – the killing off of some species leading to a reduction in diversity, the loss of good bacteria or a rise in disease-causing bad bacteria (Brennan, 2021). A dysbiotic state leads to leaky gut syndrome and inflammatory mental health conditions such as depression and anxiety (Clapp et al., 2017).

    A recent study published in the prestigious British Medical Journal, Gut reported the impact of a 12-month Mediterranean diet intervention in older people (Ghosh et al., 2020). The researchers found that participants who adhered to the diet changed their microbiomes, increasing the species associated with improved cognitive function and less inflammation. The authors concluded that improving the diet of older people to modulate the gut microbiota has the potential to promote healthier aging.

    Learn more about the microbiome

    Watch this 4-minute video produced by the prestigious scientific journal Nature about the development of our microbiome and the many roles gut microbiota play in human health, including our mental health.

    Neuroplasticity

    Until fairly recently it was scientific dogma that adult brains could not grow new neurons (nerve cells). However, in 1998 Eriksson and colleagues discovered neurogenesis (the growth of new neurons) in an area of the brain called the hippocampus. This led to the understanding that the adult brain is neuroplastic, that is, able to rewire itself. This capacity greatly enhances its function. The hippocampus is of particular interest to mental and brain health as it is involved in mood regulation (relevant to depression) as well as learning and memory (relevant to cognitive decline as we age) (Toda et al., 2019).

    Jacka and colleagues (2015) conducted the first human study using brain scans to explore the effects of diet on the brain. This study, involving 250 older Australians, confirmed results that had previously only been observed in animal studies; that lower intakes of nutrient-dense foods and higher intakes of unhealthy foods are associated with smaller left hippocampal size. This finding, that what we eat affects the size of particular brain regions (and therefore directly impacts neuroplasticity), was later replicated in a much larger study in the Netherlands involving over 4,000 participants (Croll et al., 2018).

    What this research on inflammation, the gut microbiome and neuroplasticity tells us is that nutrition affects the brain in many different ways. It is an inescapable fact that what we put in our mouths matters not just for our physical health, but for our mental and brain health also.

    Key takeaways

    • Studies from the new field of nutritional psychiatry have definitively demonstrated that consuming a high quality diet causes an improvement in symptoms of mental health conditions such as depression.
    • Research shows that the underlying mechanisms are a reduction in inflammation, an increase in the diversity of the gut microbiota and greater capacity for neuroplasticity due to reduced wasting of a brain region called the hippocampus.
    • The Mediterranean diet and traditional diets are examples of high quality diets. The Western diet provides low quality nutrition.

    Other posts you may be interested in…

    How to Break a Habit with Behavior Design

    24 January, 2023

    9 min read

    Why Mental Health is Not the Opposite of Mental Illness

    20 December, 2022

    9 min read

    Psychological Health and Safety Concepts and Terminology

    06 January, 2023

    7 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • How to Break a Habit with Behavior Design

    Managing Psychosocial Risks (Digital Badge). Free for a limited time – Access here.


    >
    Blog
    >
    How to Break a Habit with Behavior Design


    Productivity


    Self-leadership


    Wellbeing

    How to Break a Habit with Behavior Design

    wavy

    Struggling to break a habit that’s not serving your goals? Try this research-backed approach instead.

    By Well Excel. 24 January, 2023.

    9 min read

    BJ Fogg, author of the best-selling book Tiny Habits and founder of the Behavior Design Lab at Stanford University, has spent two decades researching habits. This research led him to propose the Fogg Behavior Model and a framework for change called Behavior Design (or the Tiny Habits method) (Fogg, 2020). Fogg’s methods are not based on guesswork; they’ve been road-tested on more than 60,000 people.

    The Fogg Behavior Model

    Fogg’s research has shown that all behaviors (B) arise from the same components. All of our habits, whether we label them good, bad or neutral. The components are motivation, ability and prompt. Motivation (M) is our desire to do the behavior. Ability (A) is our capacity to do the behavior. Prompt (P) is our cue to do the behavior. The model can be represented with the simple formula:

    B = MAP

    “This means behavior occurs when motivation, ability and prompt converge at the same moment,” says Fogg (2020). Figure 1 shows how each of the elements are related to one another.

    Figure 1. The Fogg Behavior Model.

    Fogg Behavior Model

    No prompt = no behavior

    Fogg (2020) reports that we experience hundreds of prompts each day and are largely unaware of them. This matters because prompts are the triggers for our habitual behaviors. Did you want to buy milk on the way home but found yourself walking through your front door without it? There was no prompt so you forgot. If you are trying to break a habit, you can use the relationship “No prompt = no behavior” to your advantage (more on this later).

    The next point to consider is do prompts always work? It turns out that the answer is “No.” We only respond reliably to prompts when they appear above the Action Line, that is, when we are sufficiently motivated and able.

    Motivation and ability have a compensatory relationship

    Fogg argues that motivation and ability have a compensatory relationship. This means the more you have of one, the less you need of the other. When our motivation is low we need to find a behavior easy to do to appear above the Action Line. To find a behavior easy requires high ability. In other words, when our motivation is low, we need high ability for a prompt to work.

    By contrast, if our motivation is high, we need less ability to fall into the region above the Action Line. That is, when our motivation is high, we can do more difficult things when prompted.

    Behavior design

    So, what does all of this mean for behavior design? The beauty of the Fogg Behavior model is that it makes it easy for us to predict whether a solution is going to work, whether it be one designed to form a new, productive habit, or quit an existing, unproductive one. The easier a behavior is to do, the more likely it is that we will do it, repeat it, and form a habit. This process is the same for good habits and bad.

    There is no universal solution for every behavior challenge. Our job is to adjust the components – M, A and P – to find the sweet spot. Behaviors that eventually become habits are those that consistently fall above the Action Line. We break habits by tweaking the components to consistently fall below the Action Line.

    Applying these insights

    This activity is adapted from an exercise Fogg designed to help people disrupt an unwanted habit (Fogg, 2020).

    1. Choose one bad habit you’d like to break.
    2. Identify the prompt for this behavior. Think of ways you could remove or avoid the prompt. If nothing comes to mind, move on to the next step.
    3. Brainstorm ways to make this behavior harder to do, thus changing your ability to perform the habit. If you can’t think of any possibilities, move on to the next step.
    4. Think of ways to lessen your motivation to do this habit. What would reduce your desire?
    5. Select an option you would actually be willing to try. Choose options as early in the sequence as possible (prompts over ability over motivation).
    6. Follow through by trialing your option. If it doesn’t work, repeat the process starting back at step 2. Fogg advises that experimenting is an important aspect of behavior design. Each person’s motivation, ability and prompts are different. And they can change, depending on the situation.

    An example in action

    Step 1: Let’s say you’re suffering financial stress from frequent, impulsive spending. This is a habit you’d like to break.

    Step 2: You consider when and where you make unplanned purchases. Often it’s in response to a notification on your phone that a favorite store is having a sale. You decide to delete the app and unsubscribe from all emails so you will receive no future prompts in relation to enticing sales.

    At the end of the month, you notice you have more money left in your checking account than usual. Win! But – you haven’t fully kicked the habit as you’ve bought a few items that attracted buyer’s remorse. You realize that when you’ve had a particularly hard day at work, you tend to swing by the mall on the way home for some retail therapy. In this case it’s not so easy to remove the prompt (a difficult day at work), so you move on to Step 3.

    Step 3: You begin to brainstorm ways to make this behavior (driving to the mall on the way home) more difficult. A few options include: carpooling so you’re no longer the driver, scheduling important appointments immediately after work so there is no time to shop on the way home, and cutting up your credit cards so it’s more challenging to pay for items.

    Step 4: You decide that none of the options above are feasible, so it’s time to consider motivation. You search for the underlying cause of the impulse buying and draw the conclusion it is usually to reduce feelings of stress rather than a true desire for the product itself. You make a list of alternative activities you could do when feeling stressed that you really enjoy such as going for a walk, phoning a friend, taking a bath and meditating.

    Step 5: You decide on phoning a friend as it’s something you’re likely to actually do. You put a Post-it note with the words “If you’re stressed, call Rebecca on your drive home” on your car dashboard.

    Step 6: One day at work, not long after making this decision, you have an extremely busy day due to several colleagues being off sick. By the time you’re walking back to your car, your stress levels are through the roof. After buckling in, you see the Post-it note and this prompts you to phone Rebecca (hands-free). Your best friend is a great distraction on the drive and you arrive home feeling in a much better mood due to sharing a few laughs. A few hours later you realize that this is when you would normally be feeling guilty, having just arrived back from the mall with purchases you can’t really afford. This realization makes you feel even better.

    Troubleshooting

    If your current strategy for breaking a bad habit isn’t working, it could be that you’ve started with the most difficult component – motivation. Start with the prompt or your ability to carry out the habitual behavior instead. You might be surprised to discover an easier path.

    Related Articles:

    • How Long Does It Take to Form a New Habit?
    • Three Myths and Truths About Habits and Goals

    Other posts you may be interested in…

    How to Sleep: Science-backed Tools and Strategies

    07 December, 2022

    10 min read

    Can You Be Too Much of a Team Player?

    02 August, 2022

    10 min read

    Fixed and Growth Mindsets: What Are Yours?

    21 August, 2022

    6 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • Deep Work and Multitasking for Knowledge Workers


    >
    Blog
    >
    Deep Work and Multitasking for Knowledge Workers


    Productivity

    Deep Work and Multitasking for Knowledge Workers

    wavy

    Multitasking is sometimes lauded as a powerful personal productivity tool. Others claim it’s not possible. What does the research say?

    By Well Excel. 16 January, 2023.

    6 min read

    Georgetown University professor Cal Newport calls “the ability to focus without distraction on a cognitively demanding task” deep work (Newport, 2016). Deep work is difficult. Indeed, Newport writes:

    “We now know from decades of research in both psychology and neuroscience that the state of mental strain that accompanies deep work is also necessary to improve your abilities” (Newport, 2016).

    Why should knowledge workers subject ourselves to this effort? Precisely because this thinking is so difficult. Deep work is “hard to replicate”, is “becoming increasingly rare” and is thus “one of the most valuable skills in our economy” (Newport, 2016). Deep work allows us to produce better results in less time and is thus central to productivity.

    Deep work and multitasking

    We can multitask. We can walk and talk, listen to a podcast while cooking, and sing while doing laundry. But when it comes to cognitive tasks, scientific studies show we can’t direct our attention to two different things at the same time very well.

    “Performing two or more tasks at the same time typically results in severe performance costs in terms of increased response latencies and/or error rates” (Fischer & Plessow, 2015).

    In other words, multitasking makes us slower and causes us to make mistakes. Cal Newport thus came to the conclusion that in order to push our “cognitive capabilities to their limit”, that is, perform deep work, we need to be in “a state of distraction-free concentration” (Newport, 2016).

    Multitasking with cognitively demanding tasks

    But why can’t we multitask when it comes to cognitively demanding tasks? The cause is a phenomenon called attention residue. University of Washington associate professor Sophie Leroy conducted research showing that when we context switch, that is, switch from one task to another, some of our attention remains focused on the initial task (Leroy, 2009). That’s why it’s not a great idea to check emails during deep work. Even if we spend only a minute on this activity, it’s not so much the lost time that’s the issue but that we’ve sacrificed precious attention in the time that follows. Multitasking divides and thus compromises our attention. And since deep work pushes us to our cognitive limits, we need all our focus.

    Leroy has also conducted research with colleague Theresa Glomb into managing attention residue caused by interruptions (Leroy & Glomb, 2018, 2020). They asked one group of participants to complete a “ready-to-resume” plan before transitioning to their next task. This group did not suffer from attention residue as they worked on the interrupting task and more readily returned to their original work compared with the participants who did not receive the planning advice. The authors propose that having a plan puts our brain at ease because it knows we will return to the task and is clear how to pick back up again. Psychologist Bluma Zeigarnik discovered a related phenomenon that plays a role in hijacking our attention, dubbed the Zeigarnik effect (Cherry, 2021). It turns out that we are able to remember unfinished tasks 90% more often than finished tasks.

    How long should we ‘deep work’ for?

    There is no scientific consensus regarding how long we can concentrate and evidence of substantial differences between individuals. In some now famous research from the 1990s, Anders Ericsson and colleagues studied the training sessions of elite performers. Their practice sessions were surprisingly short, typically between 45 and 90 minutes, though repeated a few times a day (Ericsson et al., 1993).

    A more recent study carried out by the Draugiem Group used an app to track how much time employees spent on particular tasks, and their productivity (Bradberry, 2016). This research showed that how people structured their day was more important than the number of hours worked. Employees who took short breaks were far more productive than those who worked longer hours. The magic ratio was 52 minutes of work followed by 17 minutes of rest. Notably, during the 52 minutes, the highly productive staff did not use social media or get distracted by emails; they were 100% focused on the task. When they got tired, approximately every hour, they detached from their work completely to refresh.

    Actionable, evidence-based recommendations

    The implications of the research are that you should:

    • Complete one task at a time (monotask) when undertaking deep work.
    • Deep work for as long as possible (up to around 90 minutes), within the limits of your energy and alertness, to minimize the impact of attention residue throughout the day.
    • Take regular breaks to recharge.
    • Experiment to find the deep work and rest durations that are optimal for you.
    • Finish what you’ve started before moving on to other tasks wherever you can.
    • Use “ready-to-resume” plans to manage interruptions and when you have to move on before completing an activity.
    • Expect to find deep work difficult initially but easier over time.

    More articles on productivity:

    • Personal Productivity Tools You’re (Probably) Not Using
    • Using Flow, Procrastination and Mind-wandering to Improve Creativity
    • How Long Does It Take to Form a New Habit?

    Other posts you may be interested in…

    Can You Be Too Much of a Team Player?

    02 August, 2022

    10 min read

    Personal Productivity Tools You’re (Probably) Not Using

    01 October, 2022

    8 min read

    How Long Does It Take to Form a New Habit?

    07 November, 2022

    7 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo
    rectangle-light-blue-dots

  • Recognizing Burnout in Yourself and Others


    >
    Blog
    >
    Recognizing Burnout


    Mental Health


    Productivity


    Wellbeing

    Recognizing Burnout

    wavy

    Burnout is not the same as stress. Do you know how to spot burnout in yourself or others?

    By Well Excel. 12 January, 2023.

    6 min read

    American psychologist Herbert Freudenberger is credited with popularizing the term “burnout” in the 1970s to describe the impact of severe stress on workers in the “helping professions” (Freudenberger, 1974). He noticed that dedicated doctors and nurses volunteering at a busy, free, New York City clinic would often end up exhausted and unable to cope.

    Since this initial research, burnout has been observed among stressed-out workers in many other industries and professions such as teachers, military personnel, police officers, managers, elite athletes, social workers, human service professionals, lawyers and people working in the financial sector (Heinemann & Heinemann, 2017; Poghosyan et al., 2009; Wang et al., 2020).

    Professor Christina Maslach was one of the pioneers of burnout research in the late 1970s and early 1980s and is still one of the most prominent scholars in the field. She, along with her colleague Susan Jackson, identified three dimensions of burnout (Figure 1):

    • exhaustion,
    • cynicism, and
    • inefficacy, a lack of accomplishment and reduced productivity (Maslach & Jackson, 1981).

    Dimensions of Burnout

    Figure 1. The three dimensions of burnout (Maslach & Jackson, 1981).

    Maslach and Jackson’s research led to the development of the Maslach Burnout Inventory (MBI), the first questionnaire to scientifically measure burnout (Maslach & Jackson, 1981). This tool, now in its fourth edition (Maslach et al., 2018), is still widely used by researchers today (Heinemann & Heinemann, 2017).

    The World Health Organization (WHO) publishes the International Classification of Diseases (ICD). It may surprise you to learn that “Burn-out” appeared for the first time in the latest edition, the ICD-11 (2019). This is because WHO does not consider burnout to be a medical condition. Rather, they define it as an occupational phenomenon and a factor influencing health status (World Health Organization, 2019).

    The signs and symptoms of burnout

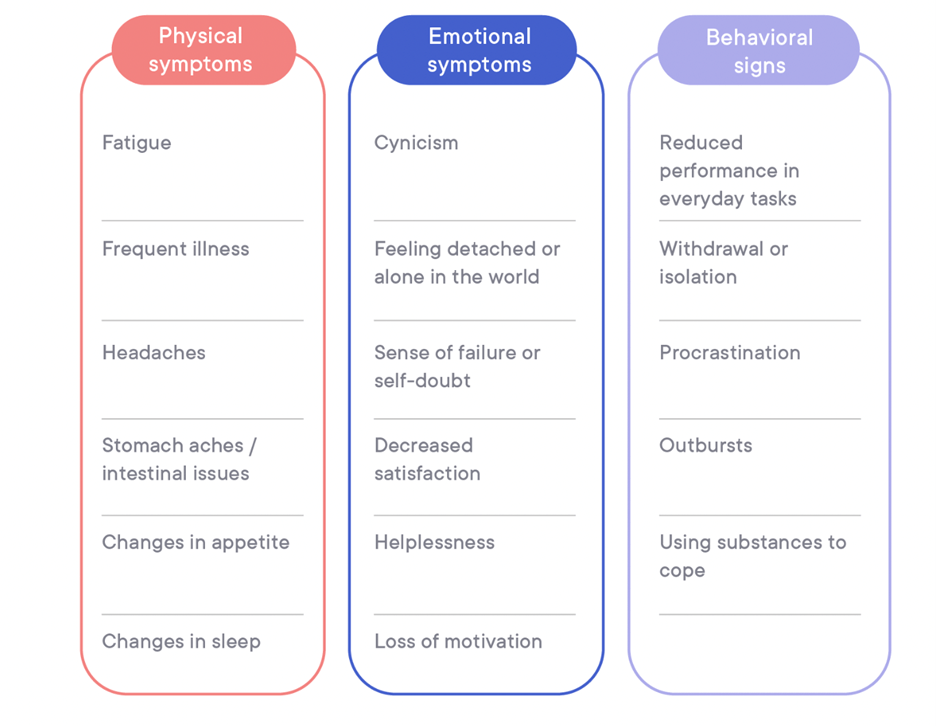
    Maslach & Jackson’s definition provides a ‘high level’ picture of burnout but may leave you wondering exactly what this phenomenon looks like in practice. Darling Downs Health, a division of Queensland Health, organizes the signs and symptoms of burnout into physical symptoms, emotional symptoms and behavioral signs (Table 1).

    Table 1. Signs and symptoms of burnout (Darling Downs Health, 2021).

    Signs and symptoms of burnout

    The personal toll of burnout – effects on the body and brain

    Burnout involves chronic activation of the body’s stress response system, otherwise known as fight-or-flight. This can lead to diseases such as diabetes, cancer and cardiovascular disease (American Psychological Association, 2018). As you are probably aware, prolonged stress also has a negative effect on the immune system which makes us susceptible to infections. This is why one of the physical symptoms listed in Table 1 is ‘frequent illness’.

    The impact of burnout is not restricted to the body. Research involving brain scans shows that “the emotional turmoil of burnout leaves a signature mark” on the brain (Michel, 2016). People formally diagnosed with burnout show differences in the amygdala, an area involved in emotional reactions, and the medial prefrontal cortex, which is involved in executive functions such as working memory, flexible thinking and self-control.

    The point here is that although burnout is not recognized as a medical condition, it does involve profound changes to the body and brain. It impacts our thoughts, feelings and behaviors and should not be ignored.

    Practical Exercise: Identifying burnout

    The Mayo Clinic (2021) has compiled a list of questions to help identify burnout based on the common signs and symptoms.

    1. Have you become cynical or critical at work?
    2. Do you drag yourself to work and have trouble getting started?
    3. Have you become irritable or impatient with co-workers, customers or clients?
    4. Do you lack the energy to be consistently productive?
    5. Do you find it hard to concentrate?
    6. Do you lack satisfaction from your achievements?
    7. Do you feel disillusioned about your job?
    8. Are you using food, drugs or alcohol to feel better or to simply not feel?
    9. Have your sleep habits changed?
    10. Are you troubled by unexplained headaches, stomach or bowel problems, or other physical complaints?

    If you answered yes to any of these questions, you might be experiencing job burnout. However, you could also have a medical condition such as depression, anxiety or chronic fatigue syndrome. The Mayo Clinic recommends talking to a doctor or a mental health provider for an accurate assessment. If your workplace has an Employee Assistance Program (EAP), consider making an appointment. If you are a leader or manager, it’s especially important to attend to your own mental health as well as that of your team.

    Key Takeaways

    • Burnout involves feelings of energy depletion or exhaustion, increased mental distance from or cynicism related to one’s job, and reduced professional efficacy.
    • According to the World Health Organization, burnout is a work-related syndrome.
    • Burnout involves physical and emotional signs and behavioral symptoms. Burnout affects both the body and the brain.
    • If you feel burned out, pay a visit to your doctor or mental health professional. Burnout should not be ignored.

    Related Reading

    • Why Mental Health is Not the Opposite of Mental Illness
    • Resilience: What It Is, What It Is Not, and Why It Matters
    • How Nutrition Impacts Your Mental Health

    Other posts you may be interested in…

    How to Sleep: Science-backed Tools and Strategies

    07 December, 2022

    10 min read

    Using Flow, Procrastination and Mind-wandering to Improve Creativity

    24 November, 2022

    9 min read

    Three Myths and Truths About Habits and Goals

    25 September, 2022

    10 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • Psychological Health and Safety Concepts and Terminology


    >
    Blog
    >
    Psychological Health and Safety Concepts and Terminology


    Mental Health


    Psych Health and Safety

    Psychological Health and Safety Concepts and Terminology

    wavy

    The regulatory landscape for workplace mental health is changing. Are you across the core ideas and language?

    By Well Excel. 06 January, 2023.

    7 min read

    In a previous article we outlined the amendments to the model work health and safety (WHS) regulations published by Safe Work Australia in April 2022. These changes were followed by the release of a model Code of Practice providing guidance on managing psychosocial hazards at work in July. Fundamentally, these changes are about employers managing risks to their workers’ mental health using the same kind of approach that has long been applied to physical safety.

    To comprehensively address risks to psychological health and safety requires leadership commitment to organization-wide approaches such as good work design and safe systems of work. This poses particular challenges due to the need to bring together leaders with different roles, experience, skill sets, knowledge and mindsets regarding WHS, such as board members, company directors, C-suite leaders, senior executives, HR leaders, work health and safety (WHS) managers, health and safety representatives (HSRs), supervisors and learning and development (L&D) professionals.

    Whichever of these roles you play in your business, it’s vital to understand psychological health and safety concepts. This post unpacks the core terminology to provide decision-making teams with a shared understanding and language.

    Mental health, psychological health and health

    The World Health Organization (WHO) defines mental health as:

    • more than the absence of mental health conditions. Rather, mental health is a state of mental wellbeing that enables people to cope with the stresses of life, to realize their abilities, to learn well and work well, and to contribute to their communities (World Health Organization, 2022a),
    • an integral part of our general health and wellbeing and a basic human right (World Health Organization, 2022b), and
    • as important as our physical health (World Health Organization, 2022b).

    Australian researchers and policy makers tend to use the term mental health (Martin et al., 2017). By contrast, the term psychological health is used in Australian WHS laws (Safe Work Australia, 2019). The two terms are interchangeable but psychological health is the preferred term when referring to legal obligations related to WHS.

    In Australian WHS laws, health includes both physical and psychological health.

    Work health and safety, occupational health and safety, and psychological health and safety

    Under Australian WHS laws employers have a legal obligation to protect workers’ health (prevent illness and disease) and protect their safety (prevent workplace injuries). Work health and safety means the management of risks to the health and safety of people in the workplace. Occupational health and safety (OH&S or OHS) is an older term for work health and safety.

    As discussed above, these obligations apply to both physical health and psychological health. Psychological health and safety is used instead of ‘mental health at work’ to emphasize mandatory WHS obligations.

    Hazards, risks and risk management

    Hazards and risks are health and safety terms that are often used interchangeably. However, this is incorrect! A hazard is a situation or thing that has the potential to harm a person whereas a risk is the possibility that harm (death, injury or illness) might occur upon exposure to a hazard (Safe Work Australia, n.d.-a). So, hazards are sources of risk. Risks take into consideration the severity of potential consequences as well as their likelihood.

    Risk management is a systematic approach to managing risks that involves four steps: (1) identifying hazards, (2) assessing risks, (3) controlling the risks, and (4) reviewing control measures (Safe Work Australia, 2022a).

    Psychosocial hazards, psychosocial risks, psychological harm and psychological injuries

    When it comes to psychosocial hazards, it’s useful to know there is not one universally agreed upon definition. Even Safe Work Australia offers several. A short definition of psychosocial hazards and factors are anything in the design or management of work that increases the risk of psychological or physical harm (Safe Work Australia, n.d.-c).

    A more comprehensive definition is hazards that:

    • arise from or in relation to:
      • the design or management of work
      • the working environment
      • plant at a workplace (machinery, equipment, tools, etc.)
      • workplace interactions or behaviors; and
    • may cause psychological or physical harm (Safe Work Australia, 2022a).

    A psychosocial risk is a risk to the health or safety of a worker or other person arising from exposure to a psychosocial hazard (Safe Work Australia, 2022b). In other words, a psychosocial risk is the likelihood that psychological harm or a psychological injury will occur from exposure to a psychosocial hazard.

    It’s important to understand that psychosocial hazards are NOT the same as psychosocial risks. This misunderstanding can occur for two reasons: (1) incorrectly believing the terms are interchangeable (i.e., that they represent the same concept), or (2) by assuming that exposure to psychosocial hazards always leads to psychosocial risks. Individual susceptibility to stressors plays a role in mental health outcomes, as does the frequency, duration and severity of exposure to psychosocial hazards.

    Psychological harm means harm to mental health (Safe Work Australia, n.d.-b). Being absent from work (absenteeism) or turning up to work but being unproductive due to psychological distress (presenteeism) are examples of psychological harm. Psychological injuries from psychosocial hazards include conditions such as anxiety, depression, burnout, post-traumatic stress disorder (PTSD), suicide and sleep disorders (Safe Work Australia, 2022a; Workplace Health and Safety Queensland, 2022).

    Key takeaways

    • All leaders within organizations, whether executives, HR professionals or WHS specialists, have an obligation to understand psychological health and safety concepts and terminology.
    • Psychological health is the term for mental health in work health and safety laws and guidance material.
    • Psychological health and safety refers to using a risk management approach to manage risks to mental health in the workplace and is a legal responsibility of Australian businesses.
    • Psychosocial hazards are anything in the design or management of work that increases the risk of psychological harm or injury (such as distress, anxiety, depression or PTSD) or physical harm (such as musculoskeletal disorders).

    Other posts you may be interested in…

    How to Identify Psychosocial Hazards

    31 October, 2022

    9 min read

    The Stigma and Shame of Loneliness

    30 November, 2022

    10 min read

    Understanding and Responding to Addiction in the Workplace

    14 December, 2022

    5 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • Understanding and Responding to Addiction at Work


    >
    Blog
    >
    Understanding and Responding to Addiction in the Workplace


    Mental Health


    Psych Health and Safety

    Understanding and Responding to Addiction in the Workplace

    wavy

    As an employer or manager, you will likely need to address addiction in the workplace at some point in your career. How are you prepared?

    By Amanda L. Giordano. 14 December, 2022.

    5 min read

    Addiction affects every facet of life, including employment. Researchers estimate that about 70% of adults with a substance use disorder are employed (Frone et al., 2022). Thus, it is likely that all employers and managers will address addiction in the workplace at some point in their careers.

    Despite its importance, being prepared to recognize and respond to addiction in the workplace can seem daunting for employers who have never had addiction training. If you are an employer or manage, here are five things that you should know if you wish respond effectively and best support employees impacted by addictions.

    Anyone can be affected by addiction in the workplace

    It is important for employers to know that addiction does not have a typical profile — it transcends demographics and social class. Anyone can develop a substance use disorder, which may be prompted or exacerbated by common risk factors such as genetics/family history, adverse childhood experiences, early exposure to drugs of abuse, and/or mental health concerns. As an employer, it’s important to not make assumptions about which employees may or may not struggle with addiction.

    Addiction is not a moral failing, but a complex disorder with biological, psychological, and environmental components

    Despite the medical community recognizing alcoholism as a disease in 1956 (Mann et al., 2020), the erroneous belief that addiction is merely the result of a character flaw, weak willpower, or antisocial personality persists in society. However, decades of research confirm that a biopsychosocial perspective of addiction, rather than a moral perspective, is most accurate. Employers must recognize that addiction is a complex disorder with a myriad of risk factors that affect its development and progression including neurobiology, genetics, life experiences, and the environment (American Society of Addiction Medicine, 2019).

    Employers should be concerned about addiction in the workplace

    Some employers and managers may believe that employees’ use of alcohol and other drugs is not their concern, however, addiction can have numerous negative occupational outcomes such as impairment at work, injury, missed work days, missed appointment and deadlines, underperforming, errors, and interpersonal difficulties. Employees spend a considerable amount of time at work and thus employers and coworkers may be among the first to recognize the signs of addiction and intervene (learn more about the important of mental health literacy at work here).

    Signs of addiction can include mood swings, chronic tardiness, difficulty concentrating, disheveled appearance, impaired coordination or slurred speech, bloodshot eyes, secretive behavior, or extreme agitation or irritability (Rupprecht, 2022). Employers should be aware of the signs of addiction and willing to broach the subject with their employees.

    Employers should be aware of substance use norms at their workplace

    Workplace celebrations, holiday parties, and out-of-office experiences may be great opportunities for social bonding among coworkers, yet they also may be times in which alcohol is readily available and used in excess (Frone et al., 2022). Employers should be cognizant of the prominence of alcohol at work events and norms related to alcohol consumption. Managers can be intentional to ensure there are a variety of beverage options, place limits on the number of alcoholic beverages served, and plan events that do not center on drinking.

    Employers should discuss addiction with employees and provide information regarding treatment options

    Rather than avoiding the issue and unintentionally contributing to the shame and stigmatization of addiction, employers should speak openly with their employees about the realities of addiction (e.g., its prevalence, etiology, progression), and describe what employees should do if they feel they have lost control over their alcohol or other drug use. Employers should provide employees with information about available Employee Assistance Programs (EAPs) and substance use disorder treatment services. If an employee recognizes they need help for substance use, they should know what to do and who to contact.

    Being an employer comes with a lot of responsibility — both for the productivity and performance of the company, and the wellness of its employees. By being informed about addiction and prepared to respond effectively, your organization can make an important contribution towards building a psychologically healthy workplace.

    About the author: Dr. Amanda L. Giordano, Ph.D., LPC, is an associate professor of counseling at the University of Georgia. She specializes in addiction counseling and has clinical, instructional, and scholarly experience related to both chemical and behavioral addictions.

    References:

    • American Society of Addiction Medicine (2019). Definition of addiction. https://www.asam.org/docs/default-source/quality-science/asam’s-2019-definition-of-addiction-(1).pdf?sfvrsn=b8b64fc2_2
    • Frone, M. R., Chosewood, L. C., Osborne, J. C., & Howard, J. J. (2022). Workplace supported recovery from substance use disorders: Defining the construct, developing a model, and proposing an agenda for future research. Occupational Health Science. Advanced online publication.
    • Mann, K., Hermann, D., & Heinz, A. (2000). One hundred years of alcoholism: The twentieth century. Alcohol and Alcoholism, 35, 10-15.
    • Rupprecht, N. (2022). The impaired anesthesia provider. Strategies to prevent, recognize, and treat substance use disorder within the workplace. AANA Journal, 90, 64-70.

    Other posts you may be interested in…

    Psychosocial Risk Assessment: Where to Start

    14 November, 2022

    7 min read

    The Stigma and Shame of Loneliness

    30 November, 2022

    10 min read

    Why Does Having Mental Health Literacy Matter?

    13 July, 2022

    6 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • Why Mental Health Is Not the Opposite of Mental Illness


    >
    Blog
    >
    Why Mental Health is Not the Opposite of Mental Illness


    Mental Health


    Psych Health and Safety


    Wellbeing

    Why Mental Health is Not the Opposite of Mental Illness

    wavy

    If we want our homes, workplaces and communities to be mentally healthy, it’s going to take more than treating mental illness.

    By Well Excel. 20 December, 2022.

    9 min read

    In 1998, the President of the American Psychological Association, Dr. Martin Seligman, gave a radical presidential address (Seligman, 2019). During this speech, and in a subsequent article in American Psychologist co-authored with Mihalyi Csikszentmihalyi (Seligman & Csikszentmihalyi, 2000), Seligman argued that psychologists were overly focused on what was wrong with people and could therefore not identify what was right. If researchers and practitioners wanted to help people reach their full potential, he said, greater emphasis needed to be given to understanding how to build positive qualities.

    The relatively new field of positive psychology, which represents a paradigm shift in psychology from a previous focus on “disorder and distress to well-being and fulfilment”, was thus born (Linley et al., 2006).

    American sociologist and psychologist Corey Keyes argued that it takes a combination of emotional, psychological and social wellbeing to be considered mentally healthy (Keyes, 2007; Keyes, 2002, 2005).

    Emotional wellbeing reflects how happy we feel and how satisfied we are with our life. Psychological wellbeing measures how well we are functioning psychologically and includes self-acceptance, personal growth, mastery over our environment and purpose in life. Social wellbeing reflects how well we are functioning socially and includes a sense of belonging to a community, making contributions to society and being accepting of human differences (Keyes, 2007).

    By analyzing data tracking positive emotions and positive functioning, Keyes came to the conclusion that mental health is not something we either have or we don’t. Mental health is better represented by a continuum than a binary (Keyes, 2002).

    Flourising and languishing: Two ends of a scale

    At the positive end of the scale is a state Keyes calls flourishing or the presence of mental health. Individuals with high mental health combine a high level of emotional wellbeing with an optimal level of psychological and social wellbeing (Keyes, 2005). To be flourishing means to be filled with positive emotions and to be functioning well psychologically and socially (Keyes, 2002).

    At the negative end of the spectrum is a state Keyes refers to as languishing or the absence of mental health. Those with poor mental health have low levels of emotional, psychological and social wellbeing (Keyes, 2005). To be languishing means that life feels empty, hollow, stagnant or one of “quiet despair” (Keyes, 2002).

    What creates the continuum is that between these two poles is a further state Keyes terms moderately mentally healthy (Keyes, 2002). Individuals who are moderately mentally healthy are neither flourishing nor languishing. The continuum is depicted as the vertical axis in Figure 1.

    Complete state model of mental health

    Figure 1. Complete state model of mental health (Mentally Healthy Workplace Alliance, 2019).

    It is possible to have a mental illness and be mentally healthy?

    What is most interesting about Keyes’s research is that he explored the question of whether mental health and mental illness are opposite ends of a single continuum (Keyes, 2005). Confirmatory factor analysis (CFA) is a type of statistical analysis commonly used in social science research to test whether data fits a particular hypothesis. Keyes’s research used CFA to test two competing theories:

    • Single-factor model: i.e., that measures of mental health and mental illness reflect a single factor as mental health and mental illness represent opposite ends of a single continuum.
    • Two-factor model: i.e., that measures of mental health are distinct from the measures of mental illness as they represent two different continua.

    Mental health was measured using scales capturing emotional, psychological and social wellbeing. Mental illness was measured using scales relating to symptoms of major depression, generalized anxiety disorder, panic disorder and alcohol dependence.

    The data strongly supported the two-factor model (Keyes, 2005). This means it is possible to have a mental illness and be mentally healthy, or to have poor mental health despite not having a mental illness.

    Case illustrations: Tracy and Peter

    Tracy was diagnosed with depression a few years ago but experiences few symptoms these days. She takes medication, sees a therapist, and works out regularly to manage her condition. Tracy enjoys her job as a manager and is considered by her team to be a capable boss. She feels her life has meaning, and has positive, close relationships with her friends and family. Tracy has a mental illness and a high level of mental health.

    Peter is one of Tracy’s direct reports. Although he has no mental illness, his mental health has been deteriorating over the last six months due to a bitter divorce and custody dispute. Tracy has noticed a substantial reduction in Peter’s performance over the last few weeks as his next court date is approaching. Peter feels unhappy most days and is extremely dissatisfied with his life and relationships. He has a low level of mental health without having a mental illness.

    Mental illness and mental health: Separate, but correlated

    A nuance in Keyes’s research is that while mental illness and mental health are distinct continua, the data shows they are correlated (Keyes, 2003). This may sound like Keyes concluded the two concepts are both related and not related. However, this is not the case. We just need to be clear about what the statistics mean.

    The results showed around one quarter of the variance between the measures of mental illness and mental health was shared variance (Keyes, 2005). This ‘modest correlation’ means that although mental illness and mental health are separate phenomena, there is a tendency for the risk of mental illness to increase as mental health decreases. For example, the risk of developing depression is over five times greater for languishing than flourishing adults (Keyes, 2007). Similarly, people with mental health conditions are more likely to experience lower levels of mental wellbeing. It’s just important to know that this is not always the case (World Health Organization, 2022).

    Keyes thus proposed that mental health should be viewed as a complete state consisting of two dimensions: the mental illness continuum (horizontal axis in Figure 1) and the mental health continuum (vertical axis). Complete mental health is a state in which individuals are both free of mental illness AND flourishing. All other states, the five remaining segments of Figure 1, represent incomplete mental health.

    Paradigm shifts: How to think about mental health

    There are several conclusions from Keyes’s research that represented fundamental shifts in how mental health and mental illness were understood at the time:

    • Mental health is not the opposite of mental illness
    • The absence of mental illness does NOT imply the presence of mental health, and the absence of mental health does not imply the presence of mental illness (Keyes, 2007).

    Keyes’s research provided an empirical basis, that is, experimental support for, Seligman’s call to action regarding our need to study what creates mental health instead of focusing solely on researching mental illness. In the two decades since the positive psychology movement was born, academics and researchers have indeed learned a great deal about human flourishing.

    Key takeaways

    • Mental illness and mental health are separate constructs.
    • Mental health is more than the absence of mental illness. To have complete mental health means to have positive feelings, positive psychological and social functioning and no mental illness.
    • Because mental illness and mental health are distinct, the prevention and treatment of mental illness will not necessarily result in more mentally healthy individuals (Keyes, 2003).
    • We can’t truly understand what it means to be mentally healthy if we only study mental illness. Positive psychology is about understanding human flourishing.
    • To learn more about positive psychology, read Martin Seligman’s book: Flourish.
    • To learn more about mental health literacy, read this blog post.

    Other posts you may be interested in…

    How is Your Financial Wellbeing?

    03 November, 2022

    8 min read

    Workplace Mental Health: The Changing Regulatory Landscape

    30 October, 2022

    6 min read

    The Stigma and Shame of Loneliness

    30 November, 2022

    10 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • How to Sleep: Science-backed Tools and Strategies


    >
    Blog
    >
    How to Sleep: Science-backed Tools and Strategies


    Mental Health


    Productivity


    Wellbeing

    How to Sleep: Science-backed Tools and Strategies

    wavy

    Practical, evidence-based tools to change your sleep behaviors to improve your health, mood and performance.

    By Well Excel. 07 December, 2022.

    10 min read

    According to the American Academy of Sleep Medicine (AASM), the term sleep hygiene refers to habits that improve our ability to fall asleep and stay asleep (AASM, 2020).

    In this article, we summarize current evidence-based sleep hygiene advice. A number of the recommendations can be found in the image below.

    Impactful sleep hygiene practices

    The importance of routine for sleep

    “Regularity is king” (Matt Walker, 2019)

    If you develop only one habit based from this article, make it this one. Sleep improves with routine as our circadian rhythm craves consistency. But how exactly do you build a healthy sleep routine? By following these steps (Blume et al., 2019; Headspace, n.d.; Lindberg, 2020; Suni, 2022d):

    • Prioritize Sleep. It can be tempting to skip sleep in favor of work, study, socializing or entertainment, but it’s critical to treat sleep as a priority.
    • Establish a consistent sleep schedule that allows for adequate sleep (7 – 9 hours). Go to sleep at the same time each day, and wake up at the same time, even on weekends.
    • Set a morning alarm and avoid hitting the snooze button, even if you haven’t slept well.
    • Establish a relaxing routine 30 – 60 minutes before bed that helps calm your body and mind allowing you to transition from wakefulness to sleep. Ideally this routine should take place somewhere other than your bedroom.
    • Get a dose of morning sunlight as soon after waking as possible. Ambient light from the environment is the most powerful “zeitgeber” (a German term that translates as “gives time”) reaching the SCN.

    Habits can take time to develop (learn more about forming habits here). The secret is to start small, be consistent, and then build on your success gradually.

    Sleep hygiene dos and don’ts

    Don’t

    • Consume caffeine (coffee, tea, soda) within 6 hours of bedtime (Drake et al., 2013). Caffeine blocks adenosine receptors making us less aware of our sleep hunger (Ribeiro & Sebastião, 2010). Caffeine also interferes with circadian melatonin rhythms which delays the onset of sleep when consumed close to bedtime (Burke et al., 2015). Not only that, but caffeine is a diuretic, meaning it stimulates urine production (Newman, 2020; Peters, 2021). Drinking caffeinated beverages late in the day makes it more likely you’ll need to use the bathroom during the night.
    • Eat a large meal before bedtime. If you’re hungry at night, eat a light, healthy snack (AASM, 2020). Eating within 3 hours of bedtime has been associated with an increased chance of waking during the night and therefore having disrupted sleep (Chung et al., 2020). Lying down shortly after eating can also lead to heartburn (Peters, 2021). It’s best to avoid foods that can trigger indigestion like citrus fruits, spicy food, fatty or fried food (Headspace, n.d.). Optimal sleep begins with a stomach that is not too full or too empty. Large meals, especially those high in fat, have been linked to sleep disorders (St-Onge et al., 2016). For tips on how to support your mental health through better nutrition, read this post.
    • Smoke cigarettes. Because nicotine is a stimulant, smoking close to bedtime can make it harder to fall asleep. Nicotine also adversely affects sleep architecture by reducing slow-wave sleep and increasing sleep disruptions (Patterson et al., 2017).
    • Use smart phones and other electronic devices within 60 – 90 minutes of bedtime. Exposure to light at night, even at very low intensities, strongly inhibits melatonin secretion and can therefore disrupt circadian rhythms (Bedrosian & Nelson, 2017; Schmid et al., 2021). Electronic screens also emit blue light which reduces restorative slow wave sleep (Schmid et al., 2021). Screens and sleep are incompatible (Headspace, n.d.). If you sleep with your phone close by, switch it to a mode that will block light and sound during the night.
    • Nap for more than 30 minutes or after late afternoon.
    • Drink alcohol before bed.

    Do

    • Manage your stress. According to the Philips 2021 report, stress is the top barrier to a good night’s sleep around the world (Philips, 2021a). The same report indicates stress regarding finances is one of the top worries (read more about how you can improve your financial wellbeing here).
    • Make your bed comfortable with a high-quality mattress, pillow, blankets and linens (Suni, 2022a).
    • Dim the lights after dark (Headspace, n.d.). See the previous point about exposure to light at night.
    • Make your bedroom quiet so that your sleep is not interrupted. You can try ear plugs, headphones or a white noise machine if it’s difficult to control noise (Suni, 2022a, 2022d).
    • Keep your bedroom cool. Most doctors recommend keeping the thermostat set between 60 to 67 degrees Fahrenheit (15.6 to 19.4 degrees Celsius) for the most comfortable sleep. A bedroom that is too warm can make it difficult to fall asleep, and lead to less time spent in slow-wave and REM sleep (Pacheco, 2022). If your bedroom doesn’t have a thermostat, heating or air-conditioning, read this article from the Sleep Foundation for ideas on controlling the temperature.
    • Exercise. Regular physical activity can improve sleep duration and quality (Dolezal et al., 2017). If you prefer exercising in the evening, there’s no need to modify your daily schedule as moderate intensity exercise up to an hour before bedtime does not adversely affect sleep (Stutz et al., 2019).
    • See a doctor if you have good sleep hygiene but continue to have trouble sleeping. You may have a sleep disorder such as insomnia or sleep apnea, or a mental health condition that is affecting your sleep (Lindberg, 2020). Your doctor may recommend medication or a sleep study to diagnose the issue.

    Sleep Myths, Tips & Takeaways

    • Feeling well-rested requires adequate sleep duration, quality sleep and appropriate timing of sleep.
    • The National Science Foundation recommends healthy adults get 7 – 9 hours of sleep per night.
    • Global surveys show that the average amount of sleep on weeknights is less than these recommendations.
    • It’s a myth that many high performers sleep less than 8 hours per night. It is rare to need fewer than the recommended hours.
    • When we are sleep deprived, we may subjectively feel fine despite being cognitively impaired.
    • Sleeping less than the recommended hours and more than the recommended hours both increase the risk of death.
    • Sleep deprivation is associated with workplace and traffic accidents.
    • We cannot train ourselves to need less sleep.
    • We cannot catch up on sleep.
    • Naps should be limited to less than 30 minutes.
    • Sleep debt is linked to weight gain and metabolic syndrome.
    • Sleep deprivation decreases our resilience.
    • Only about 1 in 2 adults globally are satisfied with their sleep.
    • Signs of sleep deprivation include feeling drowsy during the day, microsleeps, moodiness, needing more caffeine, craving junk food, feeling depressed, feeling crummy in the morning, battling breakouts, gaining weight, issues with focus and memory, eyes that are red, puffy, have dark circles or bags, falling asleep within 5 minutes of lying down, needing an alarm clock to wake up and sleeping more on days we don’t have to wake by a particular time.
    • There are significant changes in our body and our brain during each of the sleep stages. Our brain does not shut down during sleep, although there are periods when it is less active.
    • It’s normal to wake during the night, but many or extended disruptions reduce sleep quality. There are short- and long-term health consequences of poor quality sleep.
    • If you are awake for more than 20 minutes during the night, get up and do something relaxing in dim light until you’re sleepy.
    • Alcohol does not help us sleep.
    • Snoozing does not lead to meaningful additional sleep. It can assist with creativity (here are some tools to boost your creativity) but is generally not recommended.
    • There are many reasons why we sleep: energy restoration, memory consolidation, growth and repair, and waste removal.
    • Sleep is vital for the optimal performance of our immune system.
    • When we sleep matters. It is difficult to sleep out of sync with light and day due to our circadian rhythms.
    • Sleep hygiene improves our ability to fall asleep and stay asleep.

    Other posts you may be interested in…

    Does Your Workplace Mental Wellbeing Strategy Focus on Individuals?

    18 November, 2022

    6 min read

    Can You Be Too Much of a Team Player?

    02 August, 2022

    10 min read

    Understanding and Responding to Addiction in the Workplace

    04 December, 2022

    5 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • The Stigma and Shame of Loneliness


    >
    Blog
    >
    The Stigma and Shame of Loneliness


    Mental Health


    Relationships

    The Stigma and Shame of Loneliness

    wavy

    If you’re lonely and feel uncomfortable sharing this information, you are in good company. Here’s why.

    By Well Excel. 30 November, 2022.

    10 min read

    If you’re lonely and feel uncomfortable sharing this information, you are in good company. In 2018, BBC Radio 4’s program “All in the Mind” conducted The Loneliness Experiment in collaboration with researchers from The University of Manchester, Brunel University London and Exeter University. More than 55,000 people worldwide responded to the survey making The Loneliness Experiment the largest-ever study of loneliness (Manchester Institute of Education, 2018).

    The psychologists devising the questionnaire did something particularly interesting. They avoided using the words lonely or loneliness in some of the questions, and something curious happened. 30% of respondents who said they were ‘never lonely’ changed their answer when the question was asked a different way, such as whether they would like some company. These results demonstrate that many of us do not want to admit feeling lonely (Manchester Institute of Education, 2018). But why exactly?

    The survey revealed higher levels of shame among people who acknowledged their loneliness. This tells us something that we probably already know intuitively; there is a stigma surrounding the experience of loneliness (Lau & Gruen, 1992). The US Surgeon General, Dr Vivek Murthy, puts it this way:

    “People who feel lonely often are ashamed to admit it. They think it’s equivalent to admitting that they are not likable or that they’re socially insufficient in some way” (Suttie, 2020)

    Loneliness defined

    We all have a sense of what loneliness is, either from our own experience, that of those close to us, or from representations in books, movies, television, news and other forms of mass media. According to one of the researchers behind the BBC Loneliness Experiment, Professor Pamela Qualter, “what’s really striking is that people are saying loneliness is emptiness, it’s about being disconnected” (BBC Radio 4, 2018).

    People who participated in The Loneliness Experiment said that loneliness is:

    1. “Having nobody to talk to
    2. Feeling disconnected from the world
    3. Feeling left out
    4. Sadness
    5. Not feeling understood” (Hammond, 2018a).

    While it is tempting to think of loneliness as a modern-day issue, this topic has been explored by philosophers, poets, mystics and scholars for thousands of years. In the twentieth century, social scientists, psychologists and psychiatrists began to scientifically study this deeply human experience. Most recently, researchers in a new discipline called social neuroscience have turned their attention to loneliness. Social neuroscientists seek to understand how the brain mediates social processes and behavior (Nature portfolio, n.d.).

    Loneliness according to researchers

    It is useful to consider definitions from prominent loneliness researchers, in addition to what the general public understands loneliness to be, to develop a more comprehensive understanding of the phenomenon. Loneliness has variously been defined as:

    “…the exceedingly unpleasant and driving experience connected with inadequate discharge of the need for human intimacy, for interpersonal intimacy (Sullivan, 1953)

    Loneliness is caused not by being alone… Loneliness appears always to be a response to the absence of some particular type of relationship or, more accurately, a response to the absence of some particular relational provision” (Weiss, 1973)

    “…the discrepancy between a person’s desired and actual social relationships… loneliness reflects perceived social isolation” (Masi et al., 2011)

    “A subjective unpleasant or distressing feeling of a lack of connection to other people, along with a desire for more, or more satisfying, social relationships” (Badcock et al., 2022).

    “Formal definitions of loneliness vary but typically share two common elements: an emotional component (i.e., the feeling is unpleasant, unwelcome, distressing) and a social cognition component (i.e., the perception of being disconnected from other people along with a desire to be more connected)” (Badcock et al., 2022).

    Thus, according to the research, loneliness:

    • is driven by our human need to connect with one another
    • produces negative emotions
    • is a subjective state that depends on our perceptions and cognition (thinking)

    Loneliness, social isolation and solitude

    Researchers differentiate between social isolation and loneliness. Social isolation “involves the complete, or near complete, lack of contact with other people” (Ending Loneliness Together, 2021a). Social isolation is an objective state because we can count the number of relationships we have and how often we are in contact with our network. By contrast, loneliness is a subjective state reflecting our perception of being isolated (Masi et al., 2011). This may seem like semantics, but the difference is an important one.

    Because loneliness is a subjective experience, it is not easy to know who is (or isn’t) lonely (Ending Loneliness Together, 2021a). Loneliness is about feeling alone (J. T. Cacioppo et al., 2015) whereas social isolation is about actually being alone (AIHW, 2022). Clearly we can experience loneliness when we are by ourselves, but we can also feel lonely in a crowd, in our marriage or intimate relationship, when hanging out with our family, while socializing with friends, or at work (Heinrich & Gullone, 2006). As comedian Robin Williams said in the 2009 film World’s Greatest Dad: “I used to think the worst thing in life was to end up all alone. It’s not. The worst thing in life is to end up with people who make you feel all alone” (S. Cacioppo et al., 2015; Evon, 2020).

    Another emerging phrase in the scientific literature is social disconnection. This is an umbrella term covering both objective and subjective isolation, that is, social isolation and loneliness. The opposite is social connection, which the Global Initiative on Loneliness and Connection defines as: “…having a variety of relationships (from close personal ties such as family and friends through to weaker ties such as acquaintances and strangers); relationships you can rely upon for support; and relationships that are trusted, high quality, and satisfying.”

    Not everyone feels lonely when they are alone (Spithoven et al., 2019). This state is more typically referred to as solitude (S. Cacioppo et al., 2015). Whilst loneliness and social isolation are negative experiences, solitude is often an enjoyable state used for relaxation and personal growth. Although spending time in solitude involves a temporary lack of contact with people, it does not necessarily indicate social disconnection (Badcock et al., 2022).

    Tackling loneliness: Collective solutions

    The good news is that a conversation about loneliness has begun globally. In 2011 the UK launched The Campaign to End Loneliness and in 2018 appointed a Minister for Loneliness (UK Government, 2018). The charitable organization Loneliness NZ (New Zealand) began operating the same year (Loneliness NZ, 2019). 2020 was a significant year for discussions around loneliness, no doubt in part due to the devastating effect the COVID-19 pandemic had on our social lives. In Australia, a national network of universities and industry partners called Ending Loneliness Together formed (Ending Loneliness Together, 2022).

    In the United States, Dr Vivek Murthy brought attention to the importance of social connections through the publication of his book Together (Murthy, 2020) and the Coalition to End Social Isolation & Loneliness (n.d.) was formed. Finally, the Crown Princess Mary of Denmark’s foundation began a campaign to break the taboo surrounding loneliness in young people (The Mary Foundation, 2020). On January 1, 2021 the Global Initiative on Loneliness and Connection (GILC) was established with membership organizations spanning North America, South America, Europe, Asia and the Pacific (Global Initiative on Loneliness and Connection, n.d.).

    In Australia there have also been calls for a national strategy to address loneliness and social isolation. Here’s an excerpt from the submission:

    “The evidence highlights that in order to tackle loneliness effectively, there is a need to lift the stigma associated with it. Such efforts need to begin by improving community understanding and challenging public misconceptions about loneliness” (Ending Loneliness Together, 2021b).

    Other posts you may be interested in…

    How Nutrition Impacts Your Mental Health

    20 October, 2022

    8 min read

    Does IQ Predict Success in Life?

    30 September, 2022

    6 min read

    Psychosocial Risk Assessment: Where to Start

    14 November, 2022

    7 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots

  • Flow, Procrastination and Mind-wandering for Creativity


    >
    Blog
    >
    Using Flow, Procrastination and Mind-wandering to Improve Creativity


    Productivity

    Using Flow, Procrastination and Mind-wandering to Improve Creativity

    wavy

    Experiencing “Flow” – or “being in the zone” – combined with procrastination and mind-wandering can be a powerful tool to improve creativity.

    By Well Excel. 24 November, 2022.

    9 min read

    Have you come across the term “flow”, also known colloquially as “being in the zone”? It was coined by psychologist Mihaly Csikszentmihalyi to describe “a state in which people are so involved in an activity that nothing else seems to matter; the experience is so enjoyable that people will continue to do it even at great cost, for the sheer sake of doing it” (Csikszentmihalyi, 1990, p. 4). Flow is relevant because Csikszentmihalyi observed people engaged in creative work often experience flow.

    Getting to Flow: Practice

    What is often omitted from stories about creative breakthroughs are the prerequisites for flow. One of these is the skill necessary to perform the task which has been so honed through practice that it has become virtually automatic. Researcher K. Anders Ericsson studied peak performers and discovered it takes around 10,000 hours of deliberate practice to achieve mastery (Ericsson & Pool, 2016). Deliberate practice doesn’t involve engaging in an activity for the sake of enjoyment; it is practice intended to improve performance.

    Consider what it takes to become a prima ballerina – endless rehearsals with sore feet, or to become a concert pianist – hours devoted to repetitive scales. Deliberate practice is not always fun. It can be boring, frustrating and challenging. But it’s a necessary part of learning a craft, improving and developing expertise. It’s not unusual to hear of people becoming “overnight successes”. In truth, they’ve often been perfecting their craft for years before anyone noticed.

    Getting to Flow: Technical Knowledge

    The other prerequisite for flow is technical knowledge of a field. Csikszentmihalyi (1990) points out that it typically takes people 10 years before they create truly outstanding work, and this is in large part due to the time it takes to develop a deep knowledge base of their area. The more ideas we are familiar with the more chances we have to combine them in new ways. This “10-year rule” may be part of the reason that lifespan research shows creativity peaks in middle age (Velázquez et al., 2015).

    We’ve all experienced flashes of insight we call epiphanies, “a-ha! moments”, “lightbulb moments” or “eureka! moments”. Although they appear to emerge spontaneously from our unconscious minds, Csikszentmihalyi (1990) found that these insights appear only after a foundation has been laid, the skills and knowledge base we’ve just discussed. It’s a myth that passively waiting for lightbulb moments will lead to our next creative breakthrough. We need to do the hard yards first.

    Thomas Edison, the inventor of the lightbulb, explained effort plays the greatest role in innovation in his oft-cited quote: “Genius is one percent inspiration and 99 percent perspiration”. Much activity precedes a-ha! moments, and similarly, much activity follows them. We talk about “the creative process”, not isolated moments of creativity, for a reason.

    Flow, Procrastination and Mind-wandering

    But, is there anything we can do to increase our chance of having an “a-ha! moment” once we’ve taken the time to develop mastery? Yes! It turns out that these flashes of insight involve switching between different thinking modes: from a conscious, deliberate, problem-solving mode to the brain’s resting state where spontaneous, unplanned associations arise (Psychology Today, n.d.). Therefore, we can make creative insights more likely by focusing intently on a problem and then parking it to allow our minds time to daydream. Author David Burkus (2013) goes so far as to suggest that the creative process should include procrastination and mind-wandering. Ideas need time and space to incubate.

    Practical Tools: Associating and Mind-wandering

    Time to experiment and figure out what works best for you.

    1. Identify one problem in your working life that you have not yet been able to solve, something where creative “out-of-the-box thinking” might be useful.
    2. Associating: choose one (or both) of the methods below.
      • Associating using word prompts: pick a random word from a document you have quick access to. Set a timer for 3 minutes and make a list of associations between this word and your problem. Don’t judge the potential solutions, just document them. For example, let’s say your problem is to “Improve workplace culture” and your random word is “yellow”. One association could be to invite colleagues to enjoy some sunshine outdoors at lunchtime.
      • Associating using picture prompts: images are another great way to stimulate associations. Look around your home or office for a picture, then start jotting down connections to your problem no matter how tenuous they seem. For instance, if you spot a beachy photo on a co-worker’s desk, and you are still trying to solve the morale problem, then one association could be to ask everyone to use a tropical background in your next Zoom meeting to lighten the mood. Or it could be to go around the room at face-to-face meetings asking everyone to name their bucket list vacation destination. Again, aim for as many associations as possible without evaluating them at this stage.
    3. Mind-wandering: now do something to give your mind a break. Go for a brief walk, jump in the shower or take a nap. Avoid the distractions of technology during whatever downtime you choose. If such a break is not possible right now, pause the exercise. Return to it only after a mental rest so your brain has had the chance to switch modes.
    4. Did any new ideas come to you when your mind was allowed to wander? If so, write these down.
    5. Repeat the association activity with a new word or image, again with a timer set for 3 minutes.
    6. Compare your two lists. Do you notice any differences in either the number of ideas or the originality of those ideas in the before and after lists? (Creativity is typically measured in these two ways).
    7. If you observed that taking a break positively impacted your ability to think of new and useful ideas, make a note that brief periods of daydreaming can actually be highly productive.
      Place this note somewhere you’ll see often as a reminder of the value of mind-wandering to creative problem solving.
    8. Repeat steps 1 – 7 for a problem you wish to solve in your personal life.

    Key Takeaways

    • People engaged in creative work often experience flow.
    • The prerequisites for flow are skills and knowledge.
    • Peak performers develop skills through deliberate practice. It can take 10,000 hours to achieve mastery.
    • It takes around 10 years to build the knowledge base required to become an expert in a field.
    • Creativity is not just about inspiration, but hard work.
    • Creative insights occur when the brain switches between intense focus and a daydreaming, mind-wandering, rest state.

    Editor’s note: Another way to enhance your creativity is to adopt growth mindsets.

    Other posts you may be interested in…

    Fixed and Growth Mindsets: What Are Yours?

    21 August, 2022

    6 min read

    Personal Productivity Tools You’re (Probably) Not Using

    01 October, 2022

    8 min read

    Can You Be Too Much of a Team Player?

    02 August, 2022

    10 min read

    rectangle-light-blue-dots

    The next step

    The next step is to connect so we can learn about the needs of your workplace, and you can learn how Well Excel can help improve the mental health and productivity of your organisation.

    Book a Demo

    rectangle-light-blue-dots